
You can protect strength while losing weight during prescribed GLP-1 treatment. The plan has three parts. Eat protein-rich meals you can tolerate, agree a daily protein target with your clinician or dietitian that names the body weight it uses, and lift on a resistance-training routine you can keep up for the whole treatment.1
For the class-wide plan on semaglutide, tirzepatide and other GLP-1 receptor agonists, read the GLP-1 muscle-preservation guide and the GLP-1 diet guide. Lifters who want a detailed program can use the men's protein guide for preventing muscle loss on GLP-1s. The status of retatrutide next to research-only compounds is covered in Peptides for Body Recomposition.
01Separate weight loss from muscle function
Scale weight records total mass. DXA estimates fat mass, lean tissue and bone mineral, while strength tests assess what someone can do. In the STEP 1 DXA substudy, 140 adults without diabetes took semaglutide 2.4 mg or placebo for 68 weeks. Among the 95 people on semaglutide, body weight fell 15.0%, total fat mass fell 19.3% and total lean body mass fell 9.7%. Lean mass as a share of body weight rose by 3.0 percentage points because fat fell faster.2 That result comes from a conference abstract of an exploratory analysis, and it included no strength test.
DXA lean soft tissue includes water and protein in muscle, skin and other tissues.9 A 9.7% drop in that compartment is a different quantity from a 9.7% loss of contractile muscle, and neither number tells you what happened to strength.
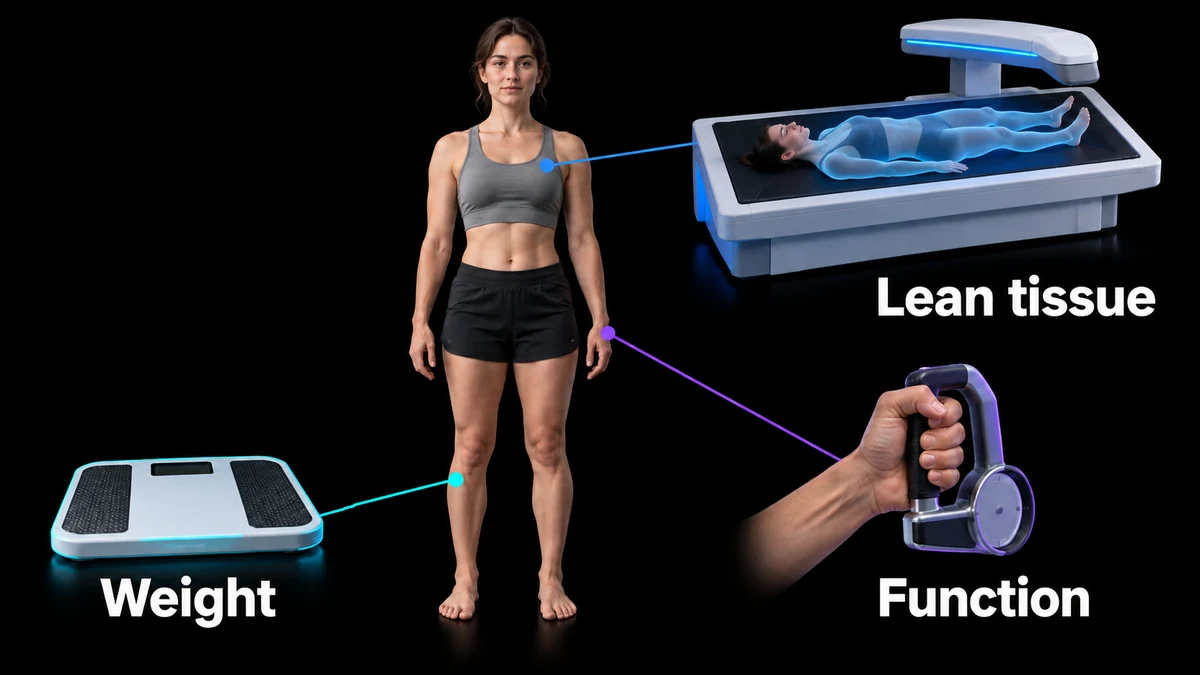
Illustration of different measurements, not a clinical scan. Scale weight measures total mass, DXA estimates tissue compartments, and a handgrip test measures one aspect of strength. None substitutes for the others.23
In SEMALEAN, handgrip strength improved while people lost weight on semaglutide. The study followed 106 adults with severe obesity through 12 months of routine semaglutide care. Lean mass fell during the first seven months and then held steady.3 Because the cohort had no control group and excluded people who stopped treatment early, it cannot show that semaglutide caused the grip change. It does show why function needs its own measurement.
Pick one or two function measures you can repeat under the same conditions, such as loads and reps on two or three lifts, a timed set of chair stands, or a flight of stairs. Record them alongside your weight. Scale weight alone cannot tell fat loss apart from strength loss.
02Retatrutide results and their limits
The new retatrutide headline comes from one population, one comparator and one way of counting results. On 28 October 2026 Lilly reported topline results from TRANSCEND-T2D-2, an open-label Phase 3 trial in 1,298 adults with type 2 diabetes taking metformin, with or without an SGLT2 inhibitor. The comparator was Ozempic 2 mg, the diabetes dose of semaglutide, rather than the 2.4 mg dose used for obesity. At 80 weeks, body weight fell 19.5% and 20.9% in the retatrutide 9 mg and 12 mg trial arms, respectively, against 9.4% with semaglutide. A1C fell 2.2 percentage points with retatrutide and 1.8 with semaglutide. Discontinuation due to adverse events was 4.8% and 7.9% with retatrutide and 2.7% with semaglutide.4
Those weight figures use the efficacy estimand. Lilly calculates it as though every randomized participant stayed on the assigned treatment for all 80 weeks, allowing interruptions or modifications, and did not start another glucose-lowering drug for more than 14 days. These are company-reported topline results, not a full peer-reviewed trial report.4
The release contains no body composition, strength, diet or protein data. Nothing in it shows that retatrutide users lose a larger share of lean tissue or need more protein per kilogram. The closest body-composition evidence is a Phase 2 substudy in adults with type 2 diabetes. Of 189 people enrolled in the body-composition substudy, 155 had a baseline DXA scan and 103 completed treatment with scans at baseline and week 36. The efficacy analysis used on-treatment data collected before drug discontinuation from randomized participants with non-missing DXA scans. The abstract does not report the analysis-set size. At week 36, total fat mass had fallen from baseline by 15.2% with pooled 4 mg doses, 26.1% with pooled 8 mg doses and 23.2% with 12 mg, compared with 2.6% on dulaglutide and 4.5% on placebo. These fat-mass comparisons come from randomized groups. The authors also judged that lean mass made up a share of total weight loss similar to other obesity treatments.5 That judgment compares the substudy with separate published studies, and the trial had no semaglutide group. It did not test protein intake, so it cannot guide a protein target. Lilly funded the trial, and all authors were Lilly employees and shareholders.
| Study | Who was studied | What it measured | What it cannot tell you |
|---|---|---|---|
| STEP 1 DXA substudy | 140 adults without diabetes, 68 weeks | Weight, fat mass and DXA lean mass with semaglutide 2.4 mg or placebo | Strength, function or protein needs2 |
| SEMALEAN | 106 adults with severe obesity, 12 months | Body composition and handgrip on semaglutide, no control group | Whether semaglutide caused the changes3 |
| Retatrutide Phase 2 substudy | 103 adults with type 2 diabetes with both scans, 36 weeks | Fat-mass changes and lean-loss share | Function, protein needs or a direct semaglutide comparison5 |
| TRANSCEND-T2D-2 | 1,298 adults with type 2 diabetes, 80 weeks | A1C and weight against Ozempic 2 mg, company topline | Body composition, strength or protein needs4 |
Retatrutide remains investigational. None of these studies compared protein prescriptions, so a larger weight-loss result does not establish a higher protein target.2345 Larger expected weight loss is a reason to watch intake and function closely. The protein target itself still depends on your body weight, health and training.
03Set a protein target with a clear weight basis
Two people who both say 1.2 g/kg can be eating 30 or 40 g of protein apart, because the advisory leaves open which body weight the grams multiply. It lists the adult RDA of 0.8 g/kg a day and notes that higher intakes of 1.2 to 1.6 g/kg a day have been proposed during active weight reduction. For people with obesity it calls the choice between actual, adjusted or ideal weight and fat-free mass unclear, and says actual weight may overestimate needs. It describes 1.5 g/kg of fat-free mass as possibly more accurate, which requires a body-composition measurement. As a simpler option it says an absolute 80 to 120 g a day may help adherence. It also advises against prolonged intake above 2 g/kg a day.1 The advisory draws on published studies and clinical experience. It is not a trial assigning people taking these medications to different protein amounts.
The arithmetic shows why the denominator matters. Take a hypothetical person who weighs 110 kg. At 1.2 g/kg of actual weight the target is 132 g. If their clinician uses an 80 kg reference weight instead, the same 1.2 g/kg gives 96 g. That 36 g gap is larger than a typical protein serving. Kidney disease or other clinical restrictions can make a generic high-protein target unsuitable, so agree the amount with the team treating you.
Write the target down in full, for example "96 g a day, which is 1.2 g/kg of an 80 kg reference weight, agreed with my dietitian in October." Ask when to recalculate it as your weight falls.
04Build meals for low appetite
On low-appetite days, record what you finish rather than what you planned. The advisory recommends building intake around protein-rich foods, choosing lower-volume nutrient-dense options, and using protein shakes when solid food is hard to manage.1 Several smaller feedings can make the daily amount easier to manage, and the leucine threshold guide covers how much per meal matters. Cottage cheese, Greek yogurt, milk and a protein shake are all compact sources.
Here is an example day for an agreed 80 g target. It uses ordinary meals and one optional drink. Yogurt and chicken values come from USDA FoodData Central records for plain nonfat Greek yogurt and roasted chicken breast, at 10.19 g and 31.02 g of protein per 100 g.67 These estimates count only the named protein sources, before the sides.
| Meal | Planned portion | Protein from named source |
|---|---|---|
| Breakfast | 150 g plain nonfat Greek yogurt with fruit | 15.3 g6 |
| Lunch | 100 g cooked chicken breast with rice and vegetables | 31.0 g7 |
| Drink if needed | 200 g plain nonfat Greek yogurt thinned with water | 20.4 g6 |
| Dinner | 50 g cooked chicken breast in a broth soup with noodles | 15.5 g7 |
| Planned total with drink | 82.2 g67 |
Without the drink, these sources provide about 61.8 g, so reaching 80 g requires another tolerated portion. A drink is one option. If you include it but eat half the lunch chicken, the planned 82.2 g falls to about 66.7 g before counting the sides. Log the portion you ate, because the gap between planned and actual intake is the information your dietitian needs. The USDA chicken record describes cooked meat. Raw breast loses water in cooking, so 100 g raw yields less than 100 g cooked. Weigh after cooking or use a raw-weight record, and stay consistent. Greek yogurts and shakes vary by brand, so use the label of the product you bought.
The table lists protein only, and a day of protein portions is not a complete diet. The rice, fruit, noodles and vegetables supply carbohydrate for training, fiber, and vitamins and minerals that a small total intake can leave short. Ask your dietitian to review energy, fiber and micronutrients on a few logged days. For more shake, bowl and soup templates, use Meal Templates for Low Appetite Days. Plan the target, log the actual, and bring the difference to your next review.
05Keep training appropriate to recovery
Resistance training is the part of the plan that protein cannot replace. The advisory states that higher protein without structured strength training is likely inadequate to preserve muscle during weight reduction, and that training plans should match each person's physical capacity.1 Walking supports health and energy expenditure and gives muscle a much smaller loading stimulus than lifting does.
Choose a resistance routine you can keep through the whole treatment, covering the major muscle groups at a frequency your recovery allows. Record loads and reps for the same few exercises each week. When sessions start to feel harder, check first what you ate that day and the day before, how you slept, and whether nausea or fatigue limited the session. A session with gastrointestinal symptoms is a reason to adjust that session. A run of weeks with falling loads is a reason to raise it with your care team.
The fat-loss muscle-preservation guide explains the training principles in more depth, and the Ozempic and Wegovy training and nutrition plan for lifters applies them to semaglutide. If you are considering creatine, read Creatine While on GLP-1.
06Review symptoms and performance together
A week of low protein reads differently depending on whether nausea, a missed session or a busy schedule caused it, so review the records side by side. Bring four things to each scheduled check-in. Bring actual protein intake against the agreed target, any symptoms and when they occurred, your repeated strength or function measures, and your weight trend. Those records help your care team investigate intake, recovery and medication tolerance. No short list of measures catches every problem.

Use the worksheet as a recording prompt. Note the amount actually eaten, symptoms and timing, and loads or repetitions from a repeatable exercise. Bring the records together at review. This illustration is not a validated diagnostic score.
Some symptoms need a clinician rather than a change to your meals. Persistent vomiting, inability to keep fluids down, severe abdominal pain or recurrent dizziness warrant prompt clinical assessment. Severe or persistent abdominal pain or inability to keep fluids down should not wait for a routine nutrition appointment.8 Any change to the medication itself is a decision for the prescriber.
Before your next appointment, find out which body weight your protein target uses, write the gram number beside it, and choose one strength measure you will repeat every week.
Footnotes
Mozaffarian D, et al. Nutritional priorities to support GLP-1 therapy for obesity: a joint Advisory from the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society. Obesity (Silver Spring). 2025, 33(8), 1475-1503, published online 30 May 2025. doi.org/10.1002/oby.24336. PubMed 40445127. A corrigendum published online 23 April 2026 corrects the description of one cited study and leaves the protein guidance unchanged. doi.org/10.1002/oby.70222
Back to textBack to text 2Back to text 3Back to text 4Back to text 5Back to text 6Wilding JPH, et al. Impact of Semaglutide on Body Composition in Adults With Overweight or Obesity: Exploratory Analysis of the STEP 1 Study. J Endocr Soc. 2021, 5(Suppl 1). Conference abstract. doi.org/10.1210/jendso/bvab048.030. PMC8089287
Back to textBack to text 2Back to text 3Back to text 4Alissou M, et al. Impact of semaglutide on fat mass, lean mass and muscle function in patients with obesity: The SEMALEAN study. Diabetes Obes Metab. 2026, 28(1), 112-121, published online 9 October 2025. doi.org/10.1111/dom.70141. PubMed 41068996
Back to textBack to text 2Back to text 3Back to text 4Eli Lilly and Company. Lilly's retatrutide delivered greater A1C reduction and more than double the weight loss of Ozempic's highest approved dose in head-to-head trial. Press release, 28 October 2026. Eli Lilly
Back to textBack to text 2Back to text 3Back to text 4Coskun T, Wu Q, Schloot NC, et al. Effects of retatrutide on body composition in people with type 2 diabetes: a substudy of a phase 2, double-blind, parallel-group, placebo-controlled, randomised trial. Lancet Diabetes Endocrinol. 2025, 13(8), 674-684, published online 30 June 2025. doi.org/10.1016/S2213-8587(25)00092-0. PubMed 40609566
Back to textBack to text 2Back to text 3US Department of Agriculture. Yogurt, Greek, plain, nonfat. FoodData Central, FDC ID 170894. FoodData Central
Back to textBack to text 2Back to text 3Back to text 4US Department of Agriculture. Chicken, broilers or fryers, breast, meat only, cooked, roasted. FoodData Central, FDC ID 171477. FoodData Central
Back to textBack to text 2Back to text 3Back to text 4Novo Nordisk. Wegovy (semaglutide) prescribing information and Medication Guide. See severe gastrointestinal adverse reactions, acute kidney injury due to volume depletion, pancreatitis and symptoms of low blood sugar. Official prescribing information
Back to textInternational Atomic Energy Agency. Dual Energy X Ray Absorptiometry for Bone Mineral Density and Body Composition Assessment. IAEA Human Health Series No. 15. Vienna, 2010, emended March 2013. See sections 2.3, 2.4 and 6.2.1. IAEA technical manual
Back to textBack to text 2
