
Food does two different jobs after an injury. While a limb cannot be loaded, meals keep protein and energy from falling with appetite, and they cannot replace the mechanical signal the muscle has lost. Once a clinician clears progressive rehabilitation, nutrition works alongside training again. Small creatine trials illustrate why that transition matters.
Hespel and colleagues put healthy young volunteers in a leg cast for two weeks, then ran ten weeks of progressive knee-extension training three times a week.1 Thigh muscle size and maximal power fell by similar amounts in the creatine and placebo groups while the leg was immobilized. Once training started, the creatine group regained both faster. That positive finding gives a useful question for the rehabilitation team. Could creatine fit the planned return to loading? During the cast, the immediate food priority is keeping intake adequate.
01Keep meals workable while movement is limited
Recovery has two nutrition states, and the clinician's loading instructions decide which one you are in. In the first, the limb is not cleared to load. Meals here need to be easy to assemble one-handed or on crutches, regular enough that protein does not disappear on bad days, and sized to an appetite that may have dropped after surgery or with pain medication. In the second, progressive rehabilitation is cleared. The same protein-containing meals continue, and carbohydrate foods help fuel the work of rehabilitation.

Illustrative meals, not targets. Both keep the same chicken and vegetables. If more food is needed as rehabilitation activity returns, an extra rice side is one option. Keep portions consistent with your care plan.13
Energy is the harder call in the first state. Movement falls, so total energy needs may fall. Surgery and wound healing add demands that differ by procedure, and the studies cited here do not set a fixed calorie cut for a person in a cast. If your care team agrees that portions need to shrink, adjust carbohydrate and fat portions while keeping the protein plan intact. Judge the change from a body-weight trend over several weeks, reviewed with your team, and avoid adjusting from one day's number.
Choose food that needs little effort to prepare. Batch-cooked chicken or tofu, tubs of Greek yogurt and cottage cheese, eggs, ready-to-drink protein shakes, microwave rice and frozen vegetables all need little standing or chopping. Any restriction from the surgical team on fluids, textures or specific foods comes before these suggestions, particularly after gastrointestinal surgery.
Wall and colleagues immobilized one leg in 24 healthy young men and measured 12 of them after five days and the other 12 after 14 days.2 Quadriceps cross-sectional area fell 3.5% at five days and 8.4% at 14 days. Leg strength fell 9.0% and 22.9%. Strength dropped more than twice as fast as size, so a leg that looks only slightly smaller can be much weaker when the cast comes off.
These were healthy volunteers in a controlled model. A postoperative patient adds surgical stress, pain, medication and often a smaller appetite, and the study cannot predict how much muscle that person will lose. The timeline still answers a practical question. Nutrition planning starts the day the cast goes on.
A muscle that stops contracting against load also responds less to the protein you eat. Wall and colleagues gave 12 healthy young men 20 g of protein before and after 14 days of one-leg immobilization. The rise in muscle protein synthesis after that feeding was 31% smaller after the cast.7 This is a disuse form of anabolic resistance. The experiment measured synthesis and did not test why it fell. Lost mechanical loading is the leading explanation, and the design leaves it untested.
Breen and colleagues found a related signal in a milder model. Healthy older adults who cut their daily steps to a sedentary level for two weeks lost leg lean mass and showed a smaller myofibrillar protein synthesis response to a 25 g egg-white protein drink.8 That trial shows the signal appears with reduced walking alone. It does not tell a younger person in a boot how large their own change will be.
Protein is still the raw material for whatever synthesis continues during immobilization. The 31% figure describes a weaker response to the same meal, and part of that response depends on contraction that food cannot supply. That is why the leucine threshold idea from training studies offers no dependable per-meal target for immobilized muscle. Wall's data show lower synthesis after disuse. They do not identify a leucine amount that immobilized muscle fails to reach.
02Protect protein when appetite falls
Low intake after surgery is common enough that the current guideline addresses it directly. The 2025 ESPEN guideline on clinical nutrition in surgery describes a prospective study of 50 patients after major abdominal surgery in which energy intake was inadequate in 82% and protein intake in 90% during the first postoperative week. Patients who missed the protein target had more serious complications.3 That group had major abdominal operations. A wrist fracture in a healthy person is a different clinical situation. Use the surgical data as a reason to check intake after a major operation.
The guideline asks clinicians to assess nutrition early, restart oral feeding as soon as possible after the operation and begin nutrition therapy as soon as risk becomes apparent. It recommends starting tube feeding within 24 hours when needs cannot be met orally, and it names patients expected to eat less than half their energy and protein needs over the next seven days as a priority group.3
Ask the surgical team or a dietitian for a protein target. Press for one when the operation is major, when you had lost weight or were eating poorly before the injury, when intake stays low afterward, or when kidney disease, complications or diet restrictions apply. If your preinjury diet met your needs, keep its protein-containing meals when activity falls and ask whether your current recovery changes those needs.
The sample day below is an illustration with weighable portions. Protein values for the yogurt, chicken and cottage cheese come from USDA FoodData Central records. The whey line uses an example label of 24 g of protein per 30 g scoop, so check the label on your own tub. The day assumes no medical restriction, and its total sets no target.
| Eating occasion | Protein anchor and portion | Protein source record | Protein |
|---|---|---|---|
| Breakfast | 250 g plain nonfat Greek yogurt with oats and fruit | FoodData Central 330137, 10.3 g per 100 g | 25.75 g |
| Lunch | 150 g raw boneless skinless chicken breast, cooked, with rice | FoodData Central 2646170, 22.5 g per 100 g raw | 33.75 g |
| Afternoon | One 30 g scoop of whey powder in water | Example label, 24 g per scoop | 24 g |
| Evening | 200 g full-fat cottage cheese with fruit | FoodData Central 2346384, 11.6 g per 100 g | 23.2 g |
| Total | Protein anchors only | 106.7 g |
Only the anchors are counted. Oats, rice and any milk add more. Spreading protein over four eating occasions follows protein distribution practice from training research, and the immobilization studies do not set a per-meal amount. If your target is higher or lower, scale the portions. On days when this volume of food feels impossible, the low-appetite meal templates use smaller and denser options, and hitting protein targets on a plant-based diet covers the same arithmetic without dairy or meat.
03What supplements can add
Essential amino acids with carbohydrate
A 28-day bed-rest trial found useful benefits from a combined nutrition intervention. Paddon-Jones and colleagues gave healthy adults 16.5 g of essential amino acids plus 30 g of carbohydrate three times a day, and compared them with a group eating mixed meals without the supplement.4 Lean leg mass was maintained in the supplement group, with a mean change of +0.2 kg, and fell 0.4 kg in controls. Leg strength fell 8.8 kg with the supplement and 17.8 kg without it. Halving the strength loss across four weeks in bed is a large effect for a drink taken three times a day.
The supplement delivered amino acids and carbohydrate together, so the trial cannot say which ingredient did the work. Bed rest also differs from a single-leg cast. Read it as evidence that nutrition strategy can change muscle outcomes during disuse. It does not set an everyday food target, and complete protein foods such as dairy, eggs, fish, poultry and soy supply the same essential amino acids within normal meals.
Leucine alone during short casts
Leucine is the amino acid most associated with switching on synthesis, so adding it to a weakened response is an intuitive idea. Two trials tested isolated leucine during leg immobilization. Backx and colleagues gave healthy young men 7.5 g of leucine a day across seven days of one-leg immobilization.10 Quadriceps cross-sectional area and strength declined in both the leucine and control groups, with no significant difference between them.
A larger 2026 trial tested a different dose and a shorter window. Churchward-Venne and colleagues studied 48 recreationally active adults, 24 young and 24 older with equal numbers of men and women, through three days of full-leg casting.11 Each participant took 5 g of leucine or 5 g of carbohydrate with each of three main meals. Daily muscle protein synthesis in the immobilized leg was about 15% lower than in the free leg in young participants and 23% lower in older participants, and leucine did not change either figure. Quadriceps cross-sectional area fell by roughly 1% in three days, with no difference between leucine and placebo.
Across these two trials, leucine alone did not preserve measured synthesis, size or strength during casts of three to seven days. They do not test longer immobilization, other doses, or leucine delivered as part of complete protein. The amino acid evidence with a positive result, from Paddon-Jones, used the full set of essential amino acids plus carbohydrate. These short-cast trials give no reason to replace complete protein foods with isolated leucine.
Omega-3 before and during immobilization
McGlory and colleagues gave 20 healthy young women 5 g a day of omega-3 fatty acids for four weeks before and two weeks during one-leg immobilization, and compared them with an isoenergetic sunflower-oil supplement.5 Muscle volume in the immobilized leg fell 8% with omega-3 and 14% with the control oil. After two weeks of normal activity, the omega-3 group had returned to baseline muscle volume and the control group had not.
The result is promising and narrow. It comes from one small trial with a four-week preloading period, which an unplanned injury rarely allows, using a specific supplement protocol rather than ordinary fish meals. The omega-3 guide explains the food and supplement sources. It was not tested around surgery. Anyone with an operation scheduled or taking anticoagulants should clear fish oil with the surgical team before starting it.
04Creatine during rehabilitation
Hespel's small trial found faster recovery of quadriceps size and maximal knee-extension power with creatine during active rehabilitation.1 After two weeks of right-leg casting, volunteers trained the knee extensors three times a week for ten weeks. Size and maximal power had fallen by similar amounts during the cast. Both recovered faster with creatine once training began. Knee-extension strength improved without a clear difference between groups in the review's account.12
This is a positive size and power finding in a reloaded muscle. Every participant trained, so the comparison tests adding creatine to rehabilitation. The trial studied healthy young volunteers rather than surgical patients.
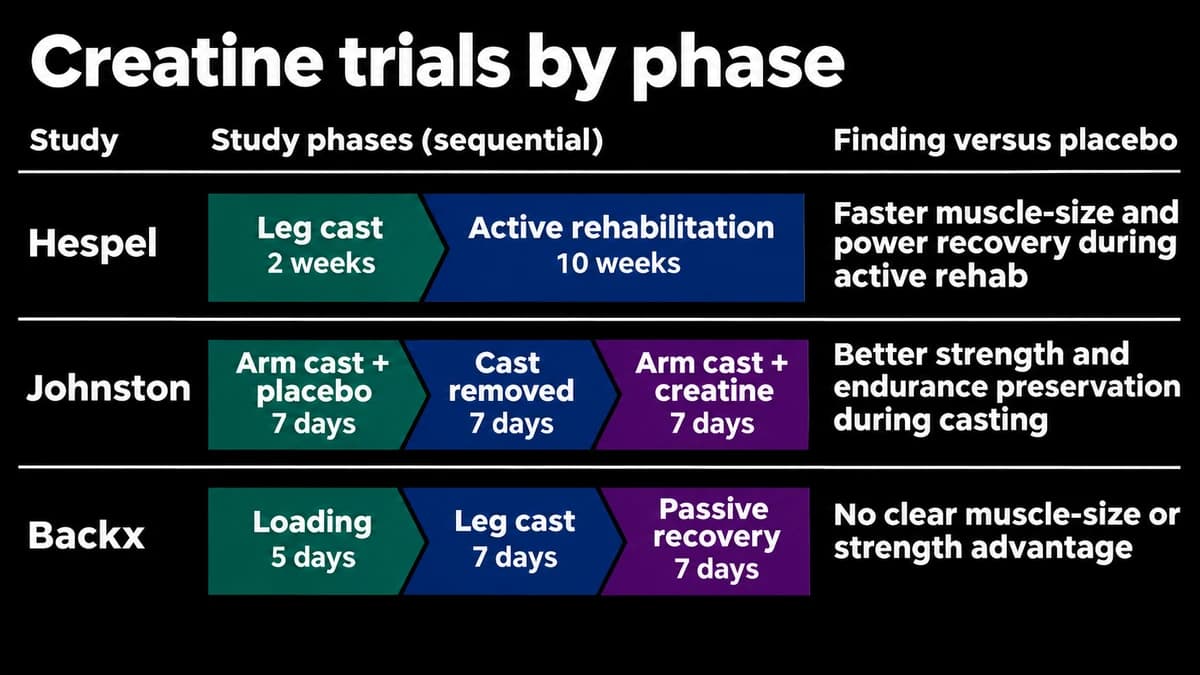
Selected phases, not to scale. Small trials in healthy young people. Johnston used a seven-man fixed-order crossover. Backx used passive recovery without structured training. No clear advantage does not establish equivalence.161213
Johnston and colleagues tested a different limb and a different question. Seven young men had an upper arm immobilized for seven days on creatine and on placebo, in a single-blind crossover with a fixed order.13 DXA lean tissue mass in the arm rose 0.9% with creatine and fell 3.7% with placebo. Elbow flexor and extensor strength and endurance also favored creatine.13 DXA lean tissue can reflect fluid changes, which matters because creatine can increase muscle water. The functional tests also favored creatine, so the finding extends beyond the DXA measurement. Seven participants tested in a fixed sequence leave substantial uncertainty.
Backx and colleagues studied the leg during the cast itself and a passive week afterward. Thirty young men were randomized to creatine or placebo and 27 completed the study. The creatine group loaded at 20 g a day for five days, then took 5 g a day through seven days of full-leg casting and seven days of recovery without structured training.6 Quadriceps cross-sectional area measured by CT fell 5.6% with creatine and 5.5% with placebo, and 1-RM strength declined in both groups. There was no statistically clear advantage during the passive recovery week either.6 This differs from Hespel's active rehabilitation. A nonsignificant difference in a small trial does not prove the effect is zero.
Pratt and colleagues collected these trials in a systematic review first published online on October 29, 2026.12 They found six placebo-controlled trials with 118 participants, mean ages 15 to 24, all using one or two weeks of limb immobilization. The synthesis was narrative, with no pooled effect estimate. Both imaging studies found similar cross-sectional area losses with creatine and placebo, while the lean-mass benefits came from DXA or bioelectrical impedance. Four trials included a recovery period and three of those used resistance rehabilitation. Two of the three reported greater gains in size or lean mass and selected function with creatine, and the third found similar recovery of maximal knee-extensor torque. The authors call the rehabilitation evidence limited. The search ran to March 2026, the newest eligible trial was from 2018, people with chronic illness were excluded, and three authors disclosed advisory, research or consulting relationships with creatine manufacturers.
If you already take creatine and tolerate it, ask your surgeon or physical therapist whether to continue through the cast and into rehabilitation, and mention any kidney condition or medication. The leg-cast trials found no statistically clear preservation advantage. The small upper-arm study found favorable functional results, and the small active-rehab studies include favorable size and power findings. Muscle comes back faster than it left places these trials alongside retraining research, and the complete guide to creatine covers dosing and safety outside injury.
05Adjust food as loading returns
Clearance for progressive loading changes the food question. The muscle is contracting against resistance again, so protein feeds a response that training is now driving, and carbohydrate supports the sessions themselves. Keep the protein anchors from the cast phase. Add oats, bread, rice, potatoes or fruit to the meal before or after rehab sessions, sized to how long the session runs and how much appetite has returned. These trials do not set an injury-specific carbohydrate dose or timing window, so use ordinary training-day judgment.
Reassess energy intake as activity returns. Early rehab sessions may be short, so the increase can be small at first. Watch session quality and the body-weight trend, and add food back gradually when sessions start to feel flat or weight keeps falling without a reason your team has agreed to.
The Hespel result came from ten weeks of structured progressive training, and every participant in both groups did that training. Treat food and supplements as support for the program your physical therapist sets. Once you are back to normal training, Muscle comes back faster than it left covers why a voluntary break recovers differently from a cast.
06Track recovery with your care team
Scale weight can hide muscle loss. Weight that holds steady through a cast can include lost muscle offset by gained fat or fluid, and the scale cannot separate them. How to tell fat loss from muscle loss covers the signals worth watching when the scale stays still.
The measurement method matters as much as the number. Research trials use CT or MRI to measure muscle cross-sectional area directly. DXA reports lean tissue, which includes water and organs as well as muscle, and bioelectrical impedance estimates lean mass from body water. Those different measurements limit a direct comparison of Johnston's DXA result with Backx's CT result. A DXA scan taken before and after can be useful if both scans use the same machine and similar hydration. Outside a trial, a tape measurement of thigh or arm girth at a marked point, the strength tests your physical therapist repeats, and functional milestones such as stairs or carrying loads track the recovery you care about.
Bring two questions to your next appointment. What protein target fits my surgery and my health? When am I cleared for progressive loading? Leave with an eating plan and a loading plan that describe the same stage of recovery.
Footnotes
Hespel P, Op't Eijnde B, Van Leemputte M, et al. Oral creatine supplementation facilitates the rehabilitation of disuse atrophy and alters the expression of muscle myogenic factors in humans. J Physiol. 2001, 536(Pt 2), 625-633. The primary abstract reports 22 volunteers and the 2026 review lists 19. The participant flow could not be verified from accessible primary full text.
Back to textBack to text 2Back to text 3Back to text 4Back to text 5Wall BT, Dirks ML, Snijders T, et al. Substantial skeletal muscle loss occurs during only 5 days of disuse. Acta Physiol (Oxf). 2014, 210(3), 600-611.
Back to textBack to text 2Weimann A, Bezmarevic M, Braga M, et al. ESPEN guideline on clinical nutrition in surgery – Update 2025. Clin Nutr. 2025, 53, 222-261. ESPEN PDF
Back to textBack to text 2Back to text 3Back to text 4Paddon-Jones D, Sheffield-Moore M, Urban RJ, et al. Essential amino acid and carbohydrate supplementation ameliorates muscle protein loss in humans during 28 days bedrest. J Clin Endocrinol Metab. 2004, 89(9), 4351-4358.
Back to textBack to text 2McGlory C, Gorissen SHM, Kamal M, et al. Omega-3 fatty acid supplementation attenuates skeletal muscle disuse atrophy during two weeks of unilateral leg immobilization in healthy young women. FASEB J. 2019, 33(3), 4586-4597.
Back to textBack to text 2Backx EMP, Hangelbroek R, Snijders T, et al. Creatine Loading Does Not Preserve Muscle Mass or Strength During Leg Immobilization in Healthy, Young Males: A Randomized Controlled Trial. Sports Med. 2017, 47(8), 1661-1671.
Back to textBack to text 2Back to text 3Back to text 4Wall BT, Snijders T, Senden JM, et al. Disuse impairs the muscle protein synthetic response to protein ingestion in healthy men. J Clin Endocrinol Metab. 2013, 98(12), 4872-4881.
Back to textBreen L, Stokes KA, Churchward-Venne TA, et al. Two weeks of reduced activity decreases leg lean mass and induces "anabolic resistance" of myofibrillar protein synthesis in healthy elderly. J Clin Endocrinol Metab. 2013, 98(6), 2604-2612.
Back to textBackx EMP, Horstman AMH, Marzuca-Nassr GN, et al. Leucine supplementation does not attenuate skeletal muscle loss during leg immobilization in healthy, young men. Nutrients. 2018, 10(5), 635.
Back to textChurchward-Venne TA, Pinckaers PJM, Smeets JJS, et al. Leucine supplementation does not attenuate the decline in daily muscle protein synthesis rates or preserve leg muscle mass during leg immobilization in young or older adults: a double-blind randomized trial. Am J Clin Nutr. 2026, 123(4), 101205. DOI
Back to textPratt J, Candow DG, Rawson ES, Forbes SC, Prokopidis K. Effects of creatine supplementation on lean mass, muscle size and muscle performance during immobilisation and rehabilitation: A systematic review. Exp Physiol. 2026. DOI
Back to textBack to text 2Back to text 3Johnston APW, Burke DG, MacNeil LG, Candow DG. Effect of creatine supplementation during cast-induced immobilization on the preservation of muscle mass, strength, and endurance. J Strength Cond Res. 2009, 23(1), 116-120.
Back to textBack to text 2Back to text 3
