
The endurance population on GLP-1 receptor agonists is growing fast and getting bad advice. Most public guidance is built for sedentary patients losing weight in a clinic, while many real users are midlife runners trying to keep zone 2 productive during weeks when early gastric emptying slows and familiar fueling stops sitting well. The collisions between standard endurance fueling and GLP-1 pharmacology are predictable. Plan your fueling and workload around how you tolerate each dose change, and training can keep moving.
01Why GLP-1s and endurance training collide
Three things change for an endurance athlete on a GLP-1 receptor agonist, and each one disrupts a system that endurance training depends on.
The first is gastric emptying. GLP-1 agonists slow the rate at which food and fluid leave the stomach, although the size and timing of that effect vary by drug, dose, duration of treatment, symptoms, and baseline gastric emptying. Hjerpsted and colleagues tested once-weekly semaglutide in 30 adults with obesity after a 12-week dose-escalation period to 1.0 mg and found delayed first-hour gastric emptying by paracetamol absorption, while overall 0 to 5 hour emptying was similar to placebo.1 Urva and colleagues found that a single dose of tirzepatide delayed gastric emptying in healthy volunteers and people with type 2 diabetes, and the effect diminished with repeated doses in the healthy group.2 Both studies measured paracetamol absorption after a meal at rest. Neither fed anyone during exercise. For a runner trying to take in 60 to 90 g of carbohydrate per hour during a long session, an early delay could still matter because carbohydrate has to leave the stomach before it can be absorbed.
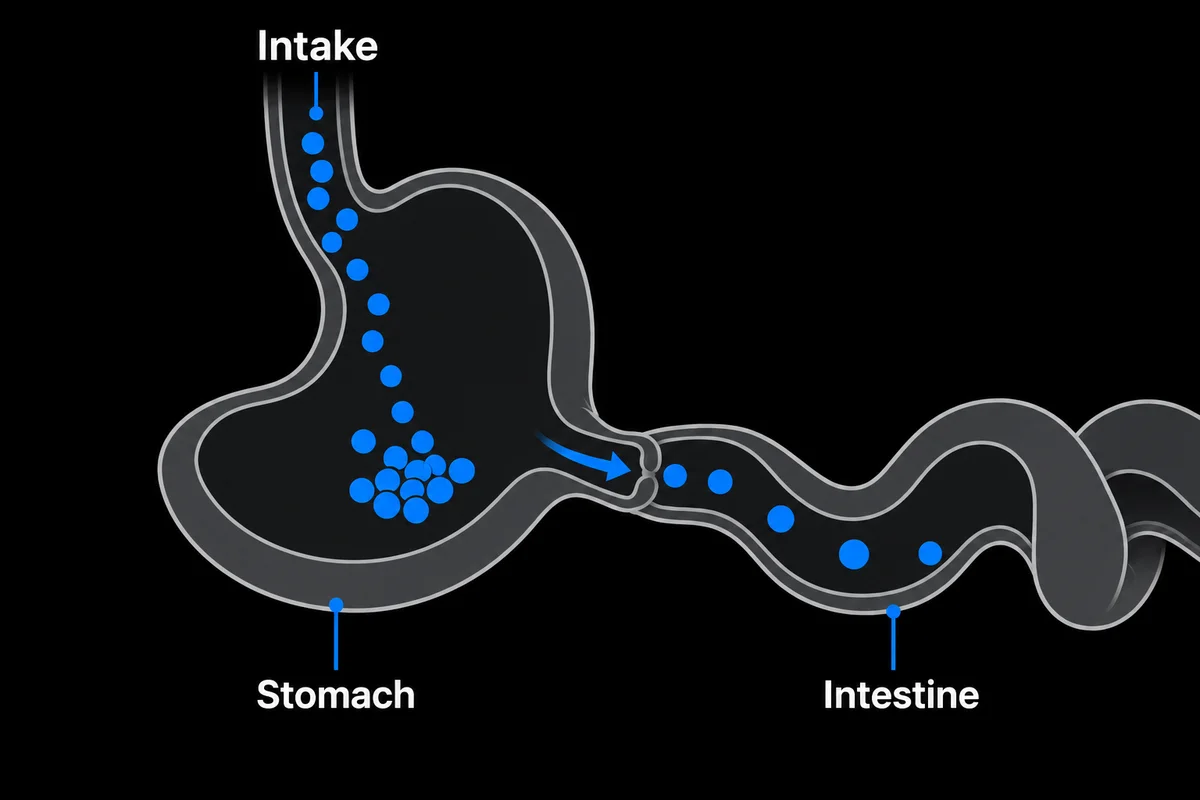
The route carbohydrate takes from stomach to intestine. The drug studies show early emptying can slow, and they say nothing about how long a particular gel or drink takes during exercise or how much is absorbed.12
The second is appetite and fluid intake. Central GLP-1 activity reduces hunger. The thirst evidence is thinner. In a three-week crossover trial of 34 patients with primary polydipsia, dulaglutide cut fluid intake by about 490 mL during an 8-hour evaluation visit. Thirst ratings were lower in a subset of 15 patients.5 A similar trial in 20 healthy volunteers found no statistically significant change in fluid intake and no difference in thirst.12 Neither trial studied athletes, exercise, semaglutide, or tirzepatide. Lower food volume also removes some of the water and sodium a normal diet carries, and sweat losses continue during training regardless.
The third is the lean-mass cost. In the semaglutide arm of the STEP 1 DXA substudy, which included 140 adults with overweight or obesity in total, lean body mass fell 9.7 percent across 68 weeks on semaglutide 2.4 mg, while lean mass as a share of body weight rose because fat mass fell further.3 In the SURMOUNT-1 DXA substudy of 160 adults, about 74 percent of the weight lost on tirzepatide was fat mass and about 26 percent was lean mass, close to the 75 and 25 percent split with placebo.4 DXA lean mass counts water, organs, and connective tissue along with skeletal muscle, so these figures describe lean tissue, a broader category than muscle. Neither substudy tested an endurance-plus-strength program designed for athletes. Resistance training provides a more specific stimulus for building and retaining skeletal muscle.9 An endurance athlete on a GLP-1 who only runs gives up the strongest training signal for keeping leg muscle while losing weight.
02Gastric emptying and the intra-workout fueling problem
Standard endurance fueling assumes the stomach behaves. Multi-transportable carbohydrate mixes can deliver about 90 g/h of usable carbohydrate when the gut is trained, the volume is reasonable, and emptying is normal.6 Higher 90 to 120 g/h protocols are covered in High-Carb Fueling at 90 to 120 g/h. On a GLP-1, that assumption may hold less well, especially around dose increases. Carbohydrate that lingers in the stomach can cause reflux, slosh, and the feeling that another gel is the last thing you want.
These gastric-emptying studies do not establish a GLP-1-specific carbohydrate reduction. The general sport benchmarks are the starting point, and your tolerance on easy sessions decides how close to them you get. The gap between two intake rates adds up faster than most athletes expect.
Compare two session fuel plans
Illustrative inputs. Compare carbohydrate consumed, with a constant hourly intake. These lines do not estimate absorption or fuel need.
Allowed input: 15–360.
Allowed input: 0–120.
Allowed input: 0–120.
A: 90 g · B: 120 g · B − A: 30 g over 120 min.
Session time (min)
View chart values
| Time (min) | A (g) | B (g) |
|---|---|---|
| 0 | 0 | 0 |
| 60 | 45 | 60 |
| 120 | 90 | 120 |
Total (g) = intake (g/h) × duration (min) ÷ 60. The input bounds are for exploring examples, not targets. General endurance guidance varies with duration, intensity and tolerance (Jeukendrup, 2014). No validated GLP-1 percentage reduction is applied. If you use insulin or insulin secretagogues, follow your diabetes team’s exercise plan before changing carbohydrate intake.
The comparison is illustrative arithmetic. At the defaults, two hours at 45 g/h totals 90 g and two hours at 60 g/h totals 120 g, a 30 g difference that is worth testing in training before it is tested on race day.
The general benchmarks come from sports-nutrition reviews of endurance athletes who were not taking GLP-1 drugs.613 Dose response holds up in controlled work. In a four-site study of 51 cyclists and triathletes, Smith and colleagues fed carbohydrate at rates up to 120 g/h during a two-hour ride followed by a 20 km time trial, and performance improved with dose up to an estimated best near 78 g/h, with smaller gains above that.14
| Session duration | General carbohydrate benchmark for endurance athletes |
|---|---|
| Under about 60 minutes | Usually no carbohydrate needed during the session |
| 1 to 2.5 hours | 30 to 60 g/h |
| Longer than 2.5 hours | 60 to 90 g/h when tolerated, with multi-transportable mixes at the top end |
Form and timing are individual. The drug studies did not compare drinks with gels or measure how long a pre-session meal stays in an athlete's stomach, so no fixed rule follows from them. If a pre-run meal still feels heavy at the start, try eating it earlier, making it smaller, or choosing lower fat and lower fiber foods, and change one thing at a time on easy sessions. If you use insulin or an insulin secretagogue such as a sulfonylurea, get an exercise glucose plan from your diabetes team before changing carbohydrate intake around training, because those drugs can cause low blood glucose when carbohydrate drops.11
For the deeper architecture of fueling around training when intake is limited, the framework in Fueling Endurance While Cutting Fat holds. The GLP-1 layer just sharpens it.
03Hydration and sodium when thirst goes quiet
When appetite and food volume drop, check how much fluid and sodium your usual meals still supply.7 Smaller meals can change both, depending on the foods you choose. Sweat losses do not shrink to match. In a dataset of 1,303 athletes tested between 2000 and 2017, endurance athletes averaged about 1.3 L of sweat per hour with wide spread between individuals.15 Sweat sodium concentration varies just as widely, and a concentration such as 800 or 1,500 mg per liter only becomes a session loss once it is multiplied by that athlete's sweat volume.8
Measure the session’s sweat loss
Example measurements, not your results. Use a short test without food, matched dry weigh-ins and measured drinks and urine. Enter 0 for none, and leave unknown measurements blank. For sodium, use a whole-body estimate from your test report. A raw regional patch reading may need conversion.
Allowed input: 20–300.
Allowed input: 20–300.
Allowed input: 0–10.
Allowed input: 0–5.
Allowed input: 15–180.
Allowed input: 0–5000. Leave blank if unknown.
1.2 L estimated sweat · 1.2 L/h
Body-mass change: -1.14%.
Sodium loss unknown. Add a whole-body sweat-sodium estimate to calculate it.
View calculation values
| Contribution | Liters |
|---|---|
| Body-mass loss | 0.8 |
| + Fluid consumed | 0.5 |
| − Urine passed | -0.1 |
| = Estimated sweat | 1.2 |
Sweat (L) ≈ before (kg) − after (kg) + drinks (L) − urine (L). Rate = sweat ÷ hours. Sodium (mg) = sweat (L) × measured sodium (mg/L). NATA’s 2017 position statement supplies the fluid equation for physically active people. Food, wet clothing, scale error and non-sweat mass losses can distort it, especially in long sessions. Repeat in comparable conditions. Neither calculated loss nor medication status is a fluid or sodium prescription. Do not aim to gain body mass during exercise.
The explorer uses the equation from the National Athletic Trainers' Association position statement. Sweat loss equals body mass before minus body mass after, plus fluid drunk, minus urine passed, and dividing by session time gives an hourly rate.16 Weigh yourself dry, towel off sweat, and wear the same minimal clothing for both weigh-ins. Skip food during a short test session so the scale change reflects fluid. The equation treats a kilogram of body-mass change as about one liter of water, then corrects for drinks and urine to estimate sweat. The result is an approximation for that session's heat, pace, clothing, and acclimation, and NATA advises repeating the test across realistic conditions because a universal hydration target does not exist.
If you enter a measured sweat sodium concentration from a sweat test, the explorer multiplies it by sweat volume to estimate sodium lost. That calculation needs a whole-body concentration. Sodium concentration varies from one skin site to another, so a raw reading from a single forearm or chest patch can sit above or below your whole-body value.8 Use a whole-body estimate from a validated method, or a patch result that has been converted with a published prediction equation. In one validation study, converted patch results matched the group average well, but individual estimates could still miss the measured whole-body value by several hundred milligrams of sodium per liter.20 Treat the sodium figure as a rough estimate. Leave it blank and sodium stays unknown, because a population average is not your number. Neither figure is a drinking or sodium prescription. Replacing every gram of loss during exercise is unnecessary for most sessions, and gaining weight across a short no-food session can warn of overdrinking. Check the measurements rather than treating the result as a reason to drink more. Excessive fluid intake can cause exercise-associated hyponatremia. NATA's 100 to 150 percent replacement range applies after exercise when the next session is less than about four hours away.16
Athletes who use saunas or heat-acclimation protocols should run the weigh-in test in the heat too, because sweat rate rises with heat. Heat exposure on top of lower food and fluid intake can leave an otherwise healthy athlete lightheaded on standing. If a sauna or hot run does that, stop the heat exposure, rest, and sip fluid. Fainting, confusion, chest pain, persistent vomiting, or symptoms that do not settle with rest need clinical assessment without delay.
04Training intensity through dose escalation
In pooled analyses of the STEP 1 to 3 semaglutide trials and the SURPASS tirzepatide trials, gastrointestinal adverse events were most common during dose escalation and declined afterward.1718 The 2024 narrative review of nutritional care emphasizes nutrition adjustments when anti-obesity medications reduce intake or trigger GI symptoms.7 The cited tolerability analyses did not test training load or establish a deload length or volume cut. The training rule is direct. Symptoms and intake set the week.
Intake stable, symptoms quiet. Train as planned.
Nausea, reflux, or low intake active. Keep the work easy and aerobic, keep strength sessions if they feel fine, and move threshold and race-pace sessions to a week when eating has settled.
Key session coming up. Rehearse its fueling on an easy session first, with the same meal, drink, and products.
Symptoms that persist. If symptoms continue across weeks, keep you from eating or drinking enough, or include repeated vomiting or dizziness, contact your prescriber or clinician instead of training around them. Severe or persistent abdominal pain, particularly with vomiting, needs prompt medical assessment. Prescribing information lists it as a possible sign of pancreatitis.21
Some weekly users notice symptoms land on particular days after the injection. The cited trials report symptoms by treatment week and do not establish a fixed post-injection window for key sessions. If your own log shows a pattern, put key sessions on the days that tolerate them and keep the injection schedule your prescriber set.
05The lean mass risk endurance athletes underestimate
A lifter on a GLP-1 has a known playbook. Hit a protein floor, train with intensity, expect strength to dip slightly, hold lean mass with the help of resistance training. The joint GLP-1 obesity advisory emphasizes that resistance or mixed training helps preserve lean mass during weight reduction, while aerobic activity alone has a smaller effect.10
The math gets uncomfortable quickly. For example, take a 78 kg recreational marathoner and assume an 18 kg loss over 12 months on tirzepatide. These are example inputs, not study results. If the loss matched the SURMOUNT-1 average split of about 26 percent lean mass, 18 × 0.26 would include about 4.7 kg of lean tissue. A group average cannot predict one runner's result, and DXA lean tissue includes water and organs as well as muscle, so the figure is no forecast of leg muscle lost. It is a reason to protect muscle on purpose.
The intervention has three parts.
The first is strength training at least three times per week, as recommended by the joint GLP-1 obesity advisory, with the plan adapted to fitness, physical capacity, and recovery. This is general obesity-care guidance, not a tested GLP-1 endurance protocol.10 Build those sessions around compound lifts for the legs and posterior chain.9 Squat or hip-hinge variations, single-leg work, calf and hamstring loading, and upper-body pulling and pressing for total-body protein synthesis. This is the same prescription a lifter would follow, layered onto an endurance week.
The second is the protein floor. Set the daily total before splitting it into meals. The 2025 joint GLP-1 obesity advisory discusses proposed intakes of 1.2 to 1.6 g/kg per day during active weight loss and notes that actual weight can overestimate needs in obesity. It also cautions against prolonged intakes at or above 2 g/kg per day.10 General resistance-training literature places much of the muscle-gain benefit around 1.6 g/kg per day, but that review does not establish a GLP-1 endurance target.9 Set the total and weight basis with a sports dietitian or clinician. Then spread it across manageable meals. For example, 1.6 g/kg per day divided into four equal meals is 0.4 g/kg per meal, an illustrative distribution rather than a guaranteed muscle protein synthesis threshold. When appetite is suppressed, hitting that floor in solid food can be impossible. The practical move is built into the low-appetite meal templates and discussed by symptom in Eating Through GLP-1 Side Effects.
The third is repeat body-composition assessment, with timing agreed with your clinician. DXA is the cleaner tool for acting on small lean-mass changes. BIA can still show direction if testing conditions are standardized, but hydration shifts make small lean-mass changes noisy. If DXA shows lean mass dropping while strength, circumference, and training quality are also sliding, the conversation moves to calorie floor, protein, and clinician review.
06Race-day fueling under delayed gastric emptying
A race on a GLP-1 is a different problem than a long training run. The fueling plan that has worked in week-to-week training may not survive race-pace cardiac output and pre-race nerves on top of delayed gastric emptying.

Race morning goes best with the meal and bottle you have already tested before hard training.
| Decision | Default approach |
|---|---|
| Race-week injection timing | Ask the prescriber how race day fits your injection schedule. Keep the schedule they set |
| Race-day pre-fuel | Use the meal, portion, and timing you have already tolerated before hard training. Lower fat and lower fiber choices are easier for many runners |
| Pre-race fluid and sodium | Repeat what you used before long training sessions. Avoid adding large volumes of fluid on race morning |
| Race-day intra-fueling | Start from the intake you have tolerated at race intensity in training, within the general duration benchmarks. Users on insulin or insulin secretagogues need glucose monitoring and a diabetes-team plan before changing race carbohydrates.11 |
| Aid station behavior | Take manageable sips and portions. Slow down at an aid station if that makes eating and drinking easier |
| Caffeine | The 3 to 6 mg/kg range comes from general exercise guidance.19 Use only an amount already tolerated in training, and reconsider caffeine when nausea, reflux, or anxiety is active |
| Bail-out plan | If nausea hits at race pace, slow to an easy effort, take small sips, and rebuild pace only as it eases. Stop and get medical help if vomiting continues or you feel faint |
If active symptoms prevent adequate intake or a full fueling rehearsal, reconsider racing and speak with your clinician. Keep the medication schedule set by your prescriber.
07A training plan that follows tolerance
Write the plan for each dose change before the injection, and let tolerance move it. The cited tolerability studies do not establish a six-week training cycle around dose changes. Let daily symptoms and intake guide the plan.
- Before the dose change. Complete key sessions while eating and drinking are stable.
- While symptoms or low intake are active. Keep training easy and aerobic. Resistance training stays in if it feels fine. Keep daily protein at the floor or slightly above.
- As eating settles. Test fueling on a controlled easy ride or run, using the meal, drink, and products you plan to use for key sessions. Bring back tempo and threshold work one session at a time.
- Before any race-relevant session. Rehearse the full fueling plan at the intended intensity in a lower-stakes workout.
- When symptoms persist. If nausea, vomiting, or low intake continue or keep you from eating and drinking enough, the conversation moves to the prescriber.
The pattern repeats with each dose step. Riding through a dose increase on willpower risks missed quality sessions and a slow lean-mass drift that the scale cannot separate from fat loss.
If treatment ends, the broader plan is in How to Stop GLP-1s Without Rapid Fat Regain. If appetite and eating patterns change, check fluid and sodium intake again. Re-run the weigh-in and rehearse race fueling once intake changes. Those two tests tell you more about your next race than any table written for someone else.
Footnotes
Hjerpsted, J. B., et al. (2018). Semaglutide improves postprandial glucose and lipid metabolism, and delays first-hour gastric emptying in subjects with obesity. Diabetes, Obesity and Metabolism, 20(3), 610–619.
Back to textBack to text 2Back to text 3Urva, S., et al. (2020). The novel dual glucose-dependent insulinotropic polypeptide and glucagon-like peptide-1 (GLP-1) receptor agonist tirzepatide transiently delays gastric emptying similarly to selective long-acting GLP-1 receptor agonists. Diabetes, Obesity and Metabolism, 22(10), 1886–1891.
Back to textBack to text 2Back to text 3Wilding, J., et al. (2021). Impact of semaglutide on body composition in adults with overweight or obesity: Exploratory analysis of the STEP 1 study. Journal of the Endocrine Society, 5(Suppl 1), A16–A17. Conference abstract. doi:10.1210/jendso/bvab048.030.
Back to textLook, M., et al. (2025). Body composition changes during weight reduction with tirzepatide in the SURMOUNT-1 study of adults with obesity or overweight. Diabetes, Obesity and Metabolism, 27(5), 2720–2729.
Back to textWinzeler, B., et al. (2021). A randomized controlled trial of the GLP-1 receptor agonist dulaglutide in primary polydipsia. Journal of Clinical Investigation, 131(20), e151800.
Back to textBack to text 2Jeukendrup, A. E. (2014). A step towards personalized sports nutrition: Carbohydrate intake during exercise. Sports Medicine, 44 Suppl 1, S25–33.
Back to textBack to text 2Almandoz, J. P., et al. (2024). Nutritional considerations with antiobesity medications. Obesity, 32(9), 1613–1631.
Back to textBack to text 2Baker, L. B. (2017). Sweating rate and sweat sodium concentration in athletes: A review of methodology and intra/interindividual variability. Sports Medicine, 47(Suppl 1), 111–128.
Back to textBack to text 2Stokes, T., Hector, A. J., Morton, R. W., McGlory, C., & Phillips, S. M. (2018). Recent perspectives regarding the role of dietary protein for the promotion of muscle hypertrophy with resistance exercise training. Nutrients, 10(2), 180.
Back to textBack to text 2Back to text 3Back to text 4Mozaffarian, D., et al. (2025). Nutritional priorities to support GLP-1 therapy for obesity: A joint advisory from the American College of Lifestyle Medicine, the American Society for Nutrition, the Obesity Medicine Association, and The Obesity Society. American Journal of Lifestyle Medicine. Co-published joint advisory.
Back to textBack to text 2Back to text 3Back to text 4American Diabetes Association. (n.d.). Understanding blood glucose and exercise. American Diabetes Association. Accessed October 15, 2026.
Back to textBack to text 2Winzeler, B., et al. (2020). Effects of glucagon-like peptide-1 receptor agonists on fluid intake in healthy volunteers. Endocrine, 70(2), 292–298.
Back to textBack to text 2Vitale, K., & Getzin, A. (2019). Nutrition and supplement update for the endurance athlete: Review and recommendations. Nutrients, 11(6), 1289.
Back to textSmith, J. W., et al. (2013). Curvilinear dose-response relationship of carbohydrate (0 to 120 g/h) and performance. Medicine and Science in Sports and Exercise, 45(2), 336–341.
Back to textBarnes, K. A., et al. (2019). Normative data for sweating rate, sweat sodium concentration, and sweat sodium loss in athletes: An update and analysis by sport. Journal of Sports Sciences, 37(20), 2356–2366.
Back to textMcDermott, B. P., et al. (2017). National Athletic Trainers' Association position statement: Fluid replacement for the physically active. Journal of Athletic Training, 52(9), 877–895.
Back to textBack to text 2Back to text 3Wharton, S., et al. (2022). Gastrointestinal tolerability of once-weekly semaglutide 2.4 mg in adults with overweight or obesity, and the relationship between gastrointestinal adverse events and weight loss. Diabetes, Obesity and Metabolism, 24(1), 94–105.
Back to textBack to text 2Patel, H., et al. (2024). Gastrointestinal adverse events and weight reduction in people with type 2 diabetes treated with tirzepatide in the SURPASS clinical trials. Diabetes, Obesity and Metabolism, 26(2), 473–481.
Back to textBack to text 2Guest, N. S., et al. (2021). International Society of Sports Nutrition position stand: Caffeine and exercise performance. Journal of the International Society of Sports Nutrition, 18, 1. doi:10.1186/s12970-020-00383-4.
Back to textBaker, L. B., et al. (2020). Cross-validation of equations to predict whole-body sweat sodium concentration from regional measures during exercise. Physiological Reports, 8(15), e14524.
Back to textEli Lilly and Company. (2026). Zepbound (tirzepatide) injection, prescribing information. Sections 5.5 and 17. Accessed November 2, 2026.
Back to text
