
A continuous glucose monitor lets an athlete without diabetes see how their own glucose responds to meals and training. Worn across several weeks, it can show patterns that repeat, such as a sharp rise after one breakfast or a dip at the same point in long sessions. It also records unexpected readings, and those readings paired with symptoms are worth bringing to a clinician. In a small 2026 study, 10 trained men who wore a sensor through two diet phases reported greater dietary awareness and personal insight from the data. Those are reports of user experience from that small group.10
A glucose trace is most useful as context beside a record of food and training. The sensor reports a tightly regulated concentration in one fluid compartment. Muscle glycogen, carbohydrate burned per hour, energy balance and recovery all sit outside that reading. Many athletes also hope the line will tell them when to take a gel or whether they recovered, and the evidence available in 2026 answers both more narrowly than the marketing does. In a small randomized cycling trial, a CGM-triggered protocol produced a steadier trace on about a third of the carbohydrate, with similar measured exertion, lactate and heart rate.5 Plan the session's fuel from established guidance, rehearse it, record what you ate and how the session went, and read the glucose trace alongside that record.
01The glucose sensor reads one fluid compartment
Blood glucose in a healthy athlete is one of the most defended numbers in the body. The liver releases glucose from its own glycogen and builds new glucose from lactate and amino acids. Insulin and glucagon adjust that release minute by minute, and working muscle pulls glucose out of the blood at rates that rise with intensity. Glucose can rise after a meal without indicating harm. A flatter trace alone does not establish better fueling or recovery.1
A CGM filament sits under the skin in interstitial fluid, the fluid between cells. Glucose has to move from capillaries into that fluid before the sensor can read it, so the reading trails blood glucose. A 2025 review of CGM in elite endurance athletes without diabetes by Helleputte, Podlogar and Gonzalez notes that this delay and the related validity concerns grow during exercise and during rapid glucose change, such as changes in exercise intensity or feeding.1 The same review states plainly that CGM does not measure muscle glycogen or carbohydrate flux.
That second limit changes how to read a flat line. A concentration is the balance between glucose entering the blood and glucose leaving it. A steady 100 mg/dL can come from a resting athlete with little uptake or from a cyclist whose liver is releasing glucose as fast as the legs are taking it up. The trace looks the same in both cases, while the glycogen left in the quadriceps can be very different.
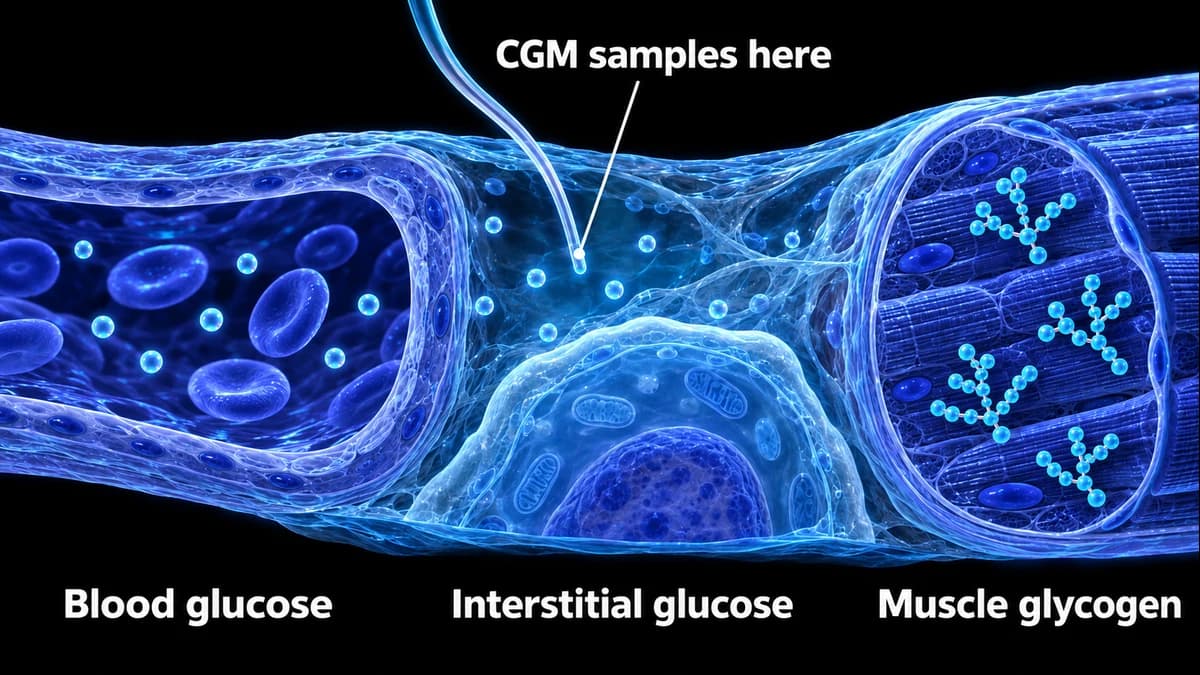
The sensor samples the fluid between cells. It cannot measure muscle glycogen stores or their restoration. Compartments, molecules and tissue are simplified and not to scale.1
| Compartment | Read by the CGM | How to interpret it |
|---|---|---|
| Interstitial fluid glucose | Yes, as an estimate | The concentration the sensor reports, trailing blood by a delay that varies with exercise and rate of change |
| Circulating blood glucose | Indirectly | Held in a narrow range by liver output, insulin and glucagon, so it can stay steady while stores fall |
| Muscle glycogen | No | Carbohydrate stored inside muscle fibers, with no direct sensor measurement of how much remains or has been restored |
Update frequency is also product-specific. When the FDA cleared the first over-the-counter CGM in March 2024, it said the app displayed glucose values and trends every 15 minutes.2 Sensor sampling, app refresh and the trend arrow are three different things, so check the current instructions for the device you own before reading any trace in real time.
Accuracy numbers belong to a specific device and protocol. A 2023 pilot by Bauhaus and colleagues compared the Abbott Libre Sense Glucose Biosensor for Sport with lab analysis of capillary blood in 10 healthy active adults under resting and running conditions, including tests after an oral glucose load.3 Its errors varied by condition. The results cannot supply one accuracy percentage for every current device or every training session.
Individual responses to the same food also differ. A 2015 study by Zeevi and colleagues tracked 800 adults across 46,898 meals and found substantial person-to-person variation in post-meal glucose to identical foods.7 This was not an athlete performance study, and it did not test whether acting on those curves improves training or racing. Treat the variation as real and the performance benefit of chasing it as untested.
02Plan the fuel before you watch the glucose line
The fuel plan comes from the session. For exercise lasting 1 to 2.5 hours, the 2016 joint position stand from the Academy of Nutrition and Dietetics, Dietitians of Canada and the American College of Sports Medicine sets a range of 30 to 60 grams of carbohydrate per hour.4 Duration, intensity, the event you are preparing for and how much your gut tolerates move you within that range. Nothing in it depends on a glucose trace.
Take a hypothetical two-hour endurance ride or run at a steady aerobic effort. A target of 45 g/h sits inside the guideline range. Split it into 15 g every 20 minutes and you get six portions, 6 × 15 = 90 grams in total, and 90 ÷ 2 hours = 45 g/h. This example uses consensus guidance and should be adjusted to your session and tolerance.
Read portions off the label of the product you will carry. A sports drink labeled 6 g of carbohydrate per 100 mL gives 15 g in 250 mL. A chew labeled 5 g each gives 15 g in three chews. The schedule below uses those hypothetical labels and starts at 10 minutes so the last portion lands before the finish.
| Planned time | Planned portion | Planned carbohydrate | Consumed | Note |
|---|---|---|---|---|
| 10 min | 250 mL drink, 6 g/100 mL | 15 g | 15 g | |
| 30 min | 250 mL drink | 15 g | 15 g | |
| 50 min | 3 chews, 5 g each | 15 g | 15 g | |
| 70 min | 250 mL drink | 15 g | 15 g | |
| 90 min | 3 chews | 15 g | 0 g | Skipped at a busy junction |
| 110 min | 250 mL drink | 15 g | 15 g | |
| Total | 90 g, 45 g/h | 75 g, 37.5 g/h |
The consumed column is the record that matters most. Planned and eaten carbohydrate drift apart in real sessions through dropped bottles, missed feeds and gut discomfort, and a glucose trace cannot tell you which of those happened. Next to the fuel record, write down duration, average pace or power for the main block, perceived exertion, gut comfort on a 0 to 10 scale, and any symptoms such as dizziness, nausea or cramping. If you wear a sensor, add the glucose trace as one more column after the session. Food logging habits from daily meals carry straight over to this kind of session record.
Take each planned portion on schedule, including when the line looks steady or is falling. The trace arrives with a delay, it does not show stores, and the trial in the next section found that a falling-trend trigger cut intake far below the guideline range.
Longer events need a different plan. Intakes above 60 g/h belong to long sessions and a gut that has been trained to handle them, covered in high-carb fueling at 90 to 120 grams per hour and gut training for race nutrition. Sessions deliberately done with less carbohydrate are a training decision made in advance, explained in carbohydrate periodization. The sensor does not make either call.
03A cycling trial changed carbohydrate timing and dose
A direct test of trend-triggered fueling comes from a 2025 randomized crossover study by Poon and colleagues in the Journal of the International Society of Sports Nutrition.5 Twelve healthy, recreationally active men without diabetes, aged 18 to 45, each rode two 75-minute trials at 50% of their measured peak power after an 8 to 12 hour fast. The paper describes the sensor as a FreeStyle Libre from Abbott without naming a generation.
In the fixed-schedule trial, riders drank 16 g of maltodextrin at 15, 30, 45 and 60 minutes, which works out to 51.2 g/h. In the CGM-informed trial, they drank carbohydrate only when the reading and trend arrow showed a qualifying fall, and took a placebo drink to match fluid otherwise. Riders averaged 1.42 carbohydrate servings, with a range of zero to three, and a mean intake of 18.1 g/h. The first serving came at an average of 31.8 minutes.
The trigger produced a steadier trace. The coefficient of variation for interstitial glucose was 8.82% in the CGM-informed trial and 11.95% on the fixed schedule. Heart rate, blood lactate and perceived exertion showed no significant difference between conditions.
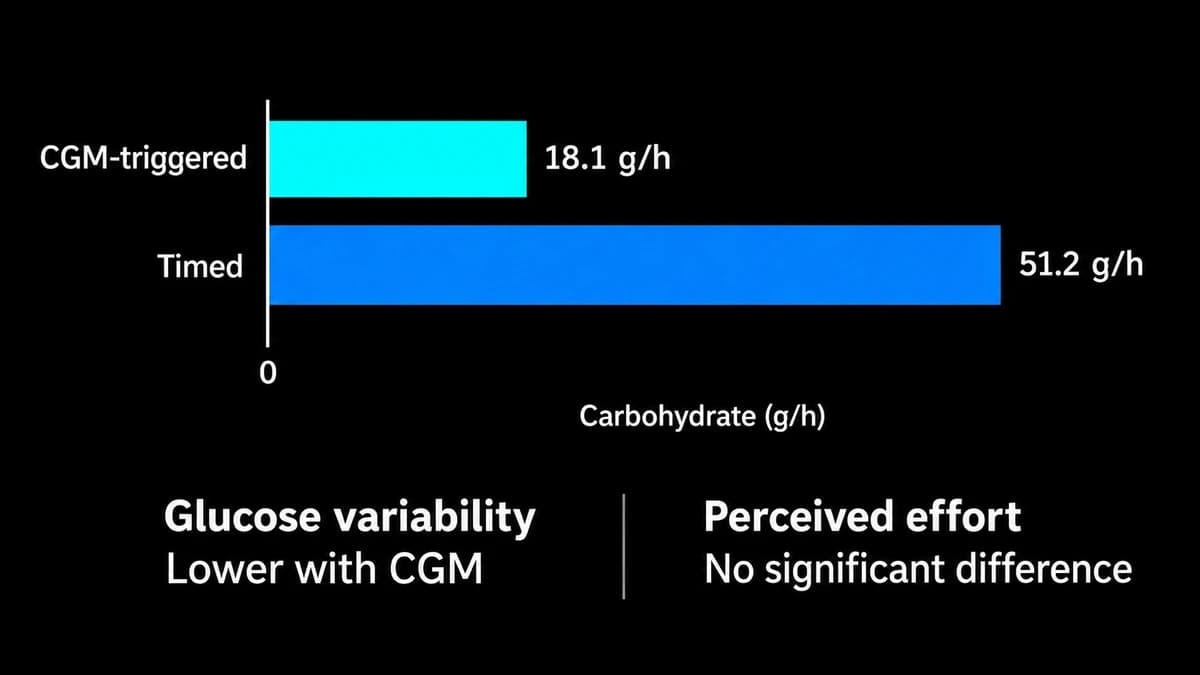
Mean intake in 12 recreationally active men during 75 minutes of cycling at 50% peak power after an overnight fast. CGM-triggered intake was 18.1 ± 10.1 g/h, versus 51.2 g/h on the timed schedule. Both dose and timing changed. The study measured glucose variability, but not race performance or muscle glycogen.5
| Measure | CGM-informed | Fixed schedule |
|---|---|---|
| Carbohydrate intake | 18.1 ± 10.1 g/h, range 0 to 38.4 | 51.2 g/h |
| Servings | 1.42 ± 0.79, range 0 to 3 | 4 |
| Glucose coefficient of variation | 8.82% | 11.95% |
| Heart rate, lactate, perceived exertion | No significant difference | No significant difference |
| Race performance and muscle glycogen | Not measured | Not measured |
The result is easy to misread as a win for less carbohydrate. The two arms differed in dose and timing at once, so the study cannot say whether the sensor, the smaller dose or the later start produced the steadier line. The ride was fixed-power, which means nobody had a chance to go faster or slower, and the authors say direct performance measures were not assessed. The sample was exploratory with no prior power calculation. The work was funded by university and foundation research grants, and the authors reported no conflicts. A lower variability number in a 75-minute fasted ride at moderate power is a finding about the trace, and 18.1 g/h is a result of this protocol, never a recommended intake.5
An October 2026 observational study by Kajisa and Sakai followed 59 highly trained male distance runners across 203 race-pace training sessions and 116 sanctioned races. Lower mean glucose was associated with reaching a pre-agreed goal time in training, but higher mean glucose was associated with reaching it in competition. The settings largely involved different athletes, and in-race carbohydrate intake was not measured. Kajisa disclosed being CEO and a shareholder of SympaFit Inc., which develops athlete monitoring technologies including CGM-based applications. These context-dependent associations do not show that CGM-guided fueling or a steadier trace improves performance.9
Bowler and colleagues' 2023 paper reviews possible sport applications and methodological considerations.8 It is useful for understanding interpretation risks, but it is not a behavior-change trial demonstrating that a sensor improves an athlete's fueling.
04A normal glucose curve does not confirm adequate fueling
Glucose regulation can keep a trace looking ordinary even when an athlete is not meeting their energy needs. The concentration alone cannot quantify the gap between food intake and training demands, or establish that recovery is adequate.1
A 2026 pilot by Matkin-Hussey and colleagues examined CGM measurements in free-living athletes.6 Nine women with relative energy deficiency in sport, diagnosed by a sports physician or reproductive endocrinologist, provided seven days of CGM and exercise data alongside nine matched healthy controls, with four days of dietary records. Mean glucose and glycemic variability did not differ between groups across 24-hour, daytime or overnight periods. The groups were small, the REDs participants were recruited from treatment and had already begun recovery, and the study was not designed to measure diagnostic accuracy. The result cannot establish diagnostic sensitivity or exclude glucose disturbances in more severe, untreated REDs. It does show why these measurements cannot be assumed to distinguish an underfueled athlete from a healthy control.
A normal-looking trace cannot rule out low energy availability, and missed periods, recurring injury, fatigue and stalled performance need a clinical assessment whatever the glucose looks like.6 Low energy availability in female endurance athletes covers the signs and the assessment pathway.
Recovery has the same problem. A post-workout curve does not report how much glycogen was restored, because the sensor has no view of muscle stores.1 Recovery fueling guidance is written in grams of carbohydrate and protein relative to body mass and the time before the next hard session, which a food log records and a trace does not.4
| Blind spot | Why glucose misses it | Useful context beyond CGM |
|---|---|---|
| Energy surplus or deficit | Glucose concentration is defended across a wide range of intakes | Logged intake paired with a weight trend |
| Macro balance | The trace carries no information on protein, fat or total calories | Food logging and macro tracking |
| Glycogen restoration after training | Muscle stores sit outside the measured compartment | Carbohydrate intake relative to the next session |
| Training context | The same rise means different things on a rest day and before intervals | Nutrition records tied to the training schedule |
| Micronutrient status | No information on iron, vitamin D or calcium | Dietary review and clinically indicated tests |
Strength athletes face a wider gap. Hypertrophy and body composition follow training stimulus, total calories, protein, sleep and adherence, and the trace measures none of those. The applied evidence discussed here does not establish that CGM-guided nutrition improves strength or body composition. A lifter gets more from tracking protein, total calories and training progress first. A sensor fits a narrower question, such as how a pre-lift meal sits, with the answer judged by how the session went.
CGM data may also have a psychological downside. USADA's athlete guidance on glucose monitoring describes dependency, guilt, reduced enjoyment and less flexibility around exercise in research on other wearables. It explicitly says that comparable effects have not been established for CGMs. If glucose data prompts you to restrict needed training carbohydrate or adds anxiety around meals, reconsider the sensor with a qualified professional.
05How to run a useful paired training comparison
In a small 2026 study by Pujol-Busquets and colleagues, 10 highly trained men without diabetes, aged 30 to 50, wore a FreeStyle Libre 2 through two 31-day diet phases, one high in carbohydrate and one low. Participants said they valued the real-time feedback, the closer attention it brought to what they ate, and the personal insights they drew from the data. They also named sensor adhesion and how often they had to scan the sensor as practical problems. These are reports of experience from a small group. The study did not test athletic performance.10
If you already wear a sensor, the most useful way to use it is a paired comparison with one practical change. Keep the route, intensity, breakfast and total carbohydrate the same across two sessions, and change one food or timing choice. The worksheet below uses the same 90 g target and swaps drink for chews in the second half. It is a proposed personal comparison, not a completed Fuel experiment. Keep total fluid similar too, replacing the drink volume with water when using chews. The amounts below illustrate how to match the comparison, not a hydration prescription.
| Variable | Session A | Session B |
|---|---|---|
| Route and duration | Same loop, 2 hours | Same loop, 2 hours |
| Intensity | Same pace or power target | Same pace or power target |
| Breakfast | Same meal, same time before the start | Same meal, same time before the start |
| Total planned carbohydrate | 90 g, 15 g every 20 minutes | 90 g, 15 g every 20 minutes |
| The one change | Drink for all six portions | Drink for the first three, chews for the last three |
| Match fluid in this example | Six 250 mL drink portions, 1.5 L total | Three 250 mL drink portions plus three 250 mL water portions, 1.5 L total |
| Record | Consumed grams, pace or power, perceived exertion, gut comfort 0 to 10, symptoms | Same measures |
| Optional | Glucose trace, read after the session | Glucose trace, read after the session |
Decide in advance which outcome answers the question. If the question is whether chews sit better in the second hour, gut comfort and consumed grams answer it. Pace or power at the same perceived effort is the performance signal. The glucose trace sits beside those as context, and a difference in the trace alone is no reason to change the plan.
Repeat the pair before trusting it. Sleep, heat, prior training load and caffeine all shift a single session, and two sessions cannot separate a food effect from a bad night. Matching curves across several pairs still would not make glucose a performance target, because the studies discussed here do not establish that steering toward a particular trace improves results.
Write the notes in the same plain terms. "My glucose rose after rice" is an observation. "Rice is bad for me" is an untested claim. "I held power better on the second hour after eating rice three hours before training instead of 30 minutes before" is a training note you can test again.
For the physiology behind why some athletes return to baseline cleanly after a meal and others do not, see metabolic flexibility, what it is, how to measure it, and how to train it. A post-meal curve is one narrow view of fuel switching, and it does not measure that capacity on its own.
A sensor is worth buying if you already know your daily calories, your protein intake and how many grams you ate in your last long session, and you have a specific question about your own glucose responses, such as how eating three hours before a session compared with 30 minutes before changes your trace, or how your glucose moves across the second hour of a long session on your usual fueling plan. Read the answer alongside gut comfort and performance. Whether chews sit better than drink can be tracked with a comfort score and a notebook, so that question alone is no reason to buy a sensor. It also suits an athlete who wants to learn their own responses to meals and training, as long as the data does not add anxiety around food. If you do not yet know those intake numbers, a food scale, a food log or a session with a sports dietitian will answer more of your questions first.
06When clinical advice comes before the sensor
A consumer CGM reading alone is not a diagnosis of hypoglycemia. Interstitial delay, measurement error and device-specific limits all sit between the number and your blood glucose, and the first FDA-cleared over-the-counter CGM was not intended for people with problematic hypoglycemia. The FDA also advised users not to make medical decisions from the output without a health professional.2 Follow the instructions and intended use for your specific device.1
Symptoms come first. Stop exercising if you feel unwell, seek medical help for concerning symptoms, and do not wait for the sensor to agree. A normal reading does not rule out a problem. Repeated unexpected low readings, symptoms that recur, or concern about glucose regulation belong with a clinician. Bring the trace together with the timing of symptoms, food intake and exercise, rather than treating the graph as a diagnosis.126
Prescribed CGM is a separate use. For people with diabetes, a care team sets individual targets and alerts and decides how readings feed into medication. This page does not cover that, and nothing here applies to insulin dosing. Athletes with diabetes should plan training fuel with their own clinician and, where possible, a sports dietitian.
Suspected underfueling also starts with a clinician. Given the REDs pilot, a sensor is the wrong first test for an athlete with missed periods, bone stress injuries or a long performance slide, and a sports physician or dietitian can assess the symptoms and intake history rather than relying on CGM as a screen.6
Bring the food and training record to that assessment too. It contains the intake, symptoms and session demands that the glucose line cannot recover for you.
Footnotes
Helleputte S, Podlogar T, Gonzalez JT. Application potential of continuous glucose monitoring (CGM) in elite endurance athletes without diabetes: What do physiology and current evidence tell us? Performance Nutrition. 2025, 1, 13. DOI 10.1186/s44410-025-00013-7. Full text
Back to textBack to text 2Back to text 3Back to text 4Back to text 5Back to text 6Back to text 7Back to text 8Back to text 9US Food and Drug Administration. FDA Clears First Over-the-Counter Continuous Glucose Monitor. Press announcement. 2024 Mar 5. FDA
Back to textBack to text 2Back to text 3Back to text 4Bauhaus H, Erdogan P, Braun H, Thevis M. Continuous Glucose Monitoring (CGM) in Sports—A Comparison between a CGM Device and Lab-Based Glucose Analyser under Resting and Exercising Conditions in Athletes. International Journal of Environmental Research and Public Health. 2023, 20(15), 6440. DOI 10.3390/ijerph20156440. PubMed · DOI
Back to textThomas DT, Erdman KA, Burke LM. Position of the Academy of Nutrition and Dietetics, Dietitians of Canada, and the American College of Sports Medicine: Nutrition and Athletic Performance. Journal of the Academy of Nutrition and Dietetics. 2016, 116(3), 501-528. DOI 10.1016/j.jand.2015.12.006. Co-published in Medicine & Science in Sports & Exercise, DOI 10.1249/MSS.0000000000000852. PubMed · ACSM DOI · Joint position paper, Table 1
Back to textBack to text 2Back to text 3Poon ETC, et al. Comparative effects of continuous glucose monitoring-informed and traditional interval-based carbohydrate refueling protocols on endurance exercise responses: an exploratory study. Journal of the International Society of Sports Nutrition. 2025, 22(1), 2561670. DOI 10.1080/15502783.2025.2561670. PMC full text · DOI
Back to textBack to text 2Back to text 3Back to text 4Back to text 5Matkin-Hussey PA, et al. Evaluating Continuous Glucose Monitoring (CGM) Derived Glucose Variability in Athletes Clinically Diagnosed With Relative Energy Deficiency in Sport (REDs). European Journal of Sport Science. 2026, 26(6), e70186. DOI 10.1002/ejsc.70186. PMC full text · DOI
Back to textBack to text 2Back to text 3Back to text 4Back to text 5Back to text 6Zeevi D, et al. Personalized Nutrition by Prediction of Glycemic Responses. Cell. 2015, 163(5), 1079-1094. DOI 10.1016/j.cell.2015.11.001. DOI · PubMed
Back to textBowler AM, et al. The Use of Continuous Glucose Monitors in Sport: Possible Applications and Considerations. International Journal of Sport Nutrition and Exercise Metabolism. 2023, 33(2), 121-132. DOI 10.1123/ijsnem.2022-0139. PubMed · DOI
Back to textKajisa T, Sakai T. In-race continuous glucose monitoring in highly trained male distance runners: a context-dependent reversal of the glucose–performance association between training and competition. Scientific Reports. 2026. DOI 10.1038/s41598-026-74914-5. Publisher full text
Back to textPujol-Busquets G, Prins PJ, Buxton J, Noakes TD, Koutnik AP. User perceptions of continuous glucose monitoring during high and low carbohydrate diets in trained, non-diabetic athletes. Science & Sports. 2026, 41(5-6), 476-483. DOI 10.1016/j.scispo.2026.03.003. Publisher abstract · DOI
Back to textBack to text 2
